
Helping podiatrists review employment and independent contractor agreements to understand compensation, malpractice insurance, termination, restrictive covenants, and post-employment obligations before signing.
When you’re presented with an associate or independent contractor agreement, whether it’s your first post-residency contract or a move across state lines, the words on the page decide more than paychecks: they shape your professional autonomy, patient relationships, and long-term career options. We wrote this guide to give podiatrists clear, practical guidance on the contract terms that matter most.
Drawing on decades of contract review experience at Chelle Law and Robert Chelle’s national practice, we explain common agreement types, compensation mechanics, malpractice and tail issues, state-specific variations (especially around noncompetes and classification), and the practical edits that protect your income and ability to practice. Read on to learn the questions you should be asking, the red flags to watch for, and when it’s time to consult an attorney.
Key Takeaways
- Understanding your podiatrist contract attorney’s advice helps you recognize the type of agreement—employment, independent contractor, or professional service—which affects your compensation and liability.
- Clear compensation terms, including definitions of collections, pay timing, and expense deductions, are crucial to protect your income as a podiatrist.
- Classification as an employee or independent contractor has major tax, benefit, and malpractice coverage implications; improper classification carries legal risks.
- Noncompetes and restrictive covenants vary widely by state; negotiating a narrow geographic scope, reasonable duration, and carve-outs preserves your future practice options.
- Ensure malpractice insurance and tail coverage responsibilities are clearly spelled out to avoid significant post-employment liabilities.
- Before signing, review termination clauses, repayment obligations, patient records access, and continuity of care provisions for fairness and protection of your professional autonomy.
Types Of Agreements Podiatrists Commonly Sign
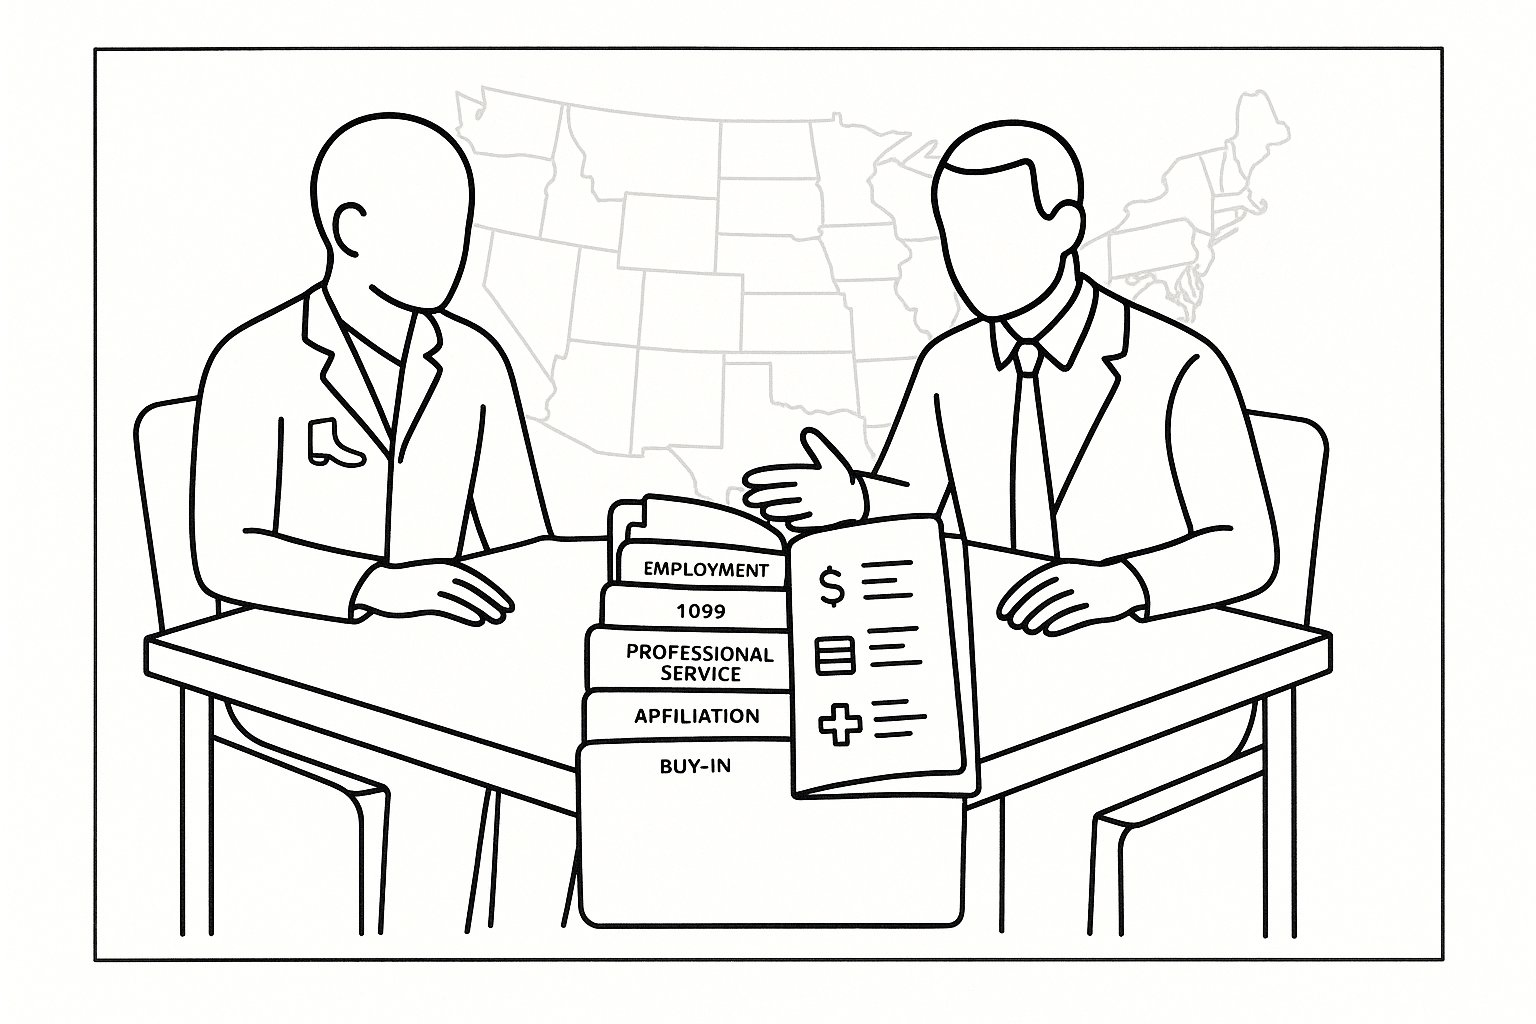
Podiatrists typically encounter a handful of agreement types. Knowing which one you’ve been offered matters because the document defines compensation, liability, scope of practice, and post-separation obligations.
Employment agreements (W-2): The employer controls scheduling, billing, supervision rules, and often sets clinical protocols. Hospitals, multispecialty clinics, and many private podiatry practices prefer employment agreements because they can control billing practices, credentialing, and supervision while offering benefits like group malpractice coverage and an employer-paid share of benefits. Employment agreements commonly include noncompetes, mandatory benefit contributions, and employer-directed patient assignment.
Independent contractor agreements (1099): These are common in offices, some private podiatry surgical centers, and locum/temporary arrangements. Independent contractor status offers more autonomy but increases personal responsibility for malpractice coverage, taxes, and compliance. States increasingly scrutinize contractor arrangements: misclassification risks can result in wage-and-hour claims, tax liabilities, and penalties.
Professional service contracts: Larger orthopedic groups, hospital-employed podiatrists, and multispecialty clinics sometimes use hybrid professional service agreements in which a professional corporation (PC/PA) enters into a contract with a health system. These can blend employment features with service-fee provisions and often include precise production-share formulas and administrative fee deductions.
Buy-in, partnership, and shareholder agreements: For podiatrists pursuing ownership in group practices or ambulatory surgery centers, buy-in agreements describe valuation, earning adjustments, buyout mechanics, and restrictive covenants. These agreements raise unique issues: how goodwill is calculated, how debt is assumed, and what happens to clinical schedules and hospital privileges if the practice is sold.
State-by-state nuance: Employers structure these deals differently across the U.S. Hospitals and health systems in some states prefer direct employment with hospital-sponsored malpractice occurrence coverage; in others, they use professional services agreements to sidestep employment obligations while still imposing clinic control. Groups often use standard-form contractor agreements nationwide but modify them to comply with state professional ownership, fee-splitting, or supervision rules.
Practical tip: Before signing, identify the agreement type, confirm who bills (you or the practice), who holds patient records, and whether the practice requires you to maintain hospital privileges or specific ancillary services. Those operational details determine both day-to-day practice and long-term liabilities.
Key Contract Terms That Protect Your Compensation
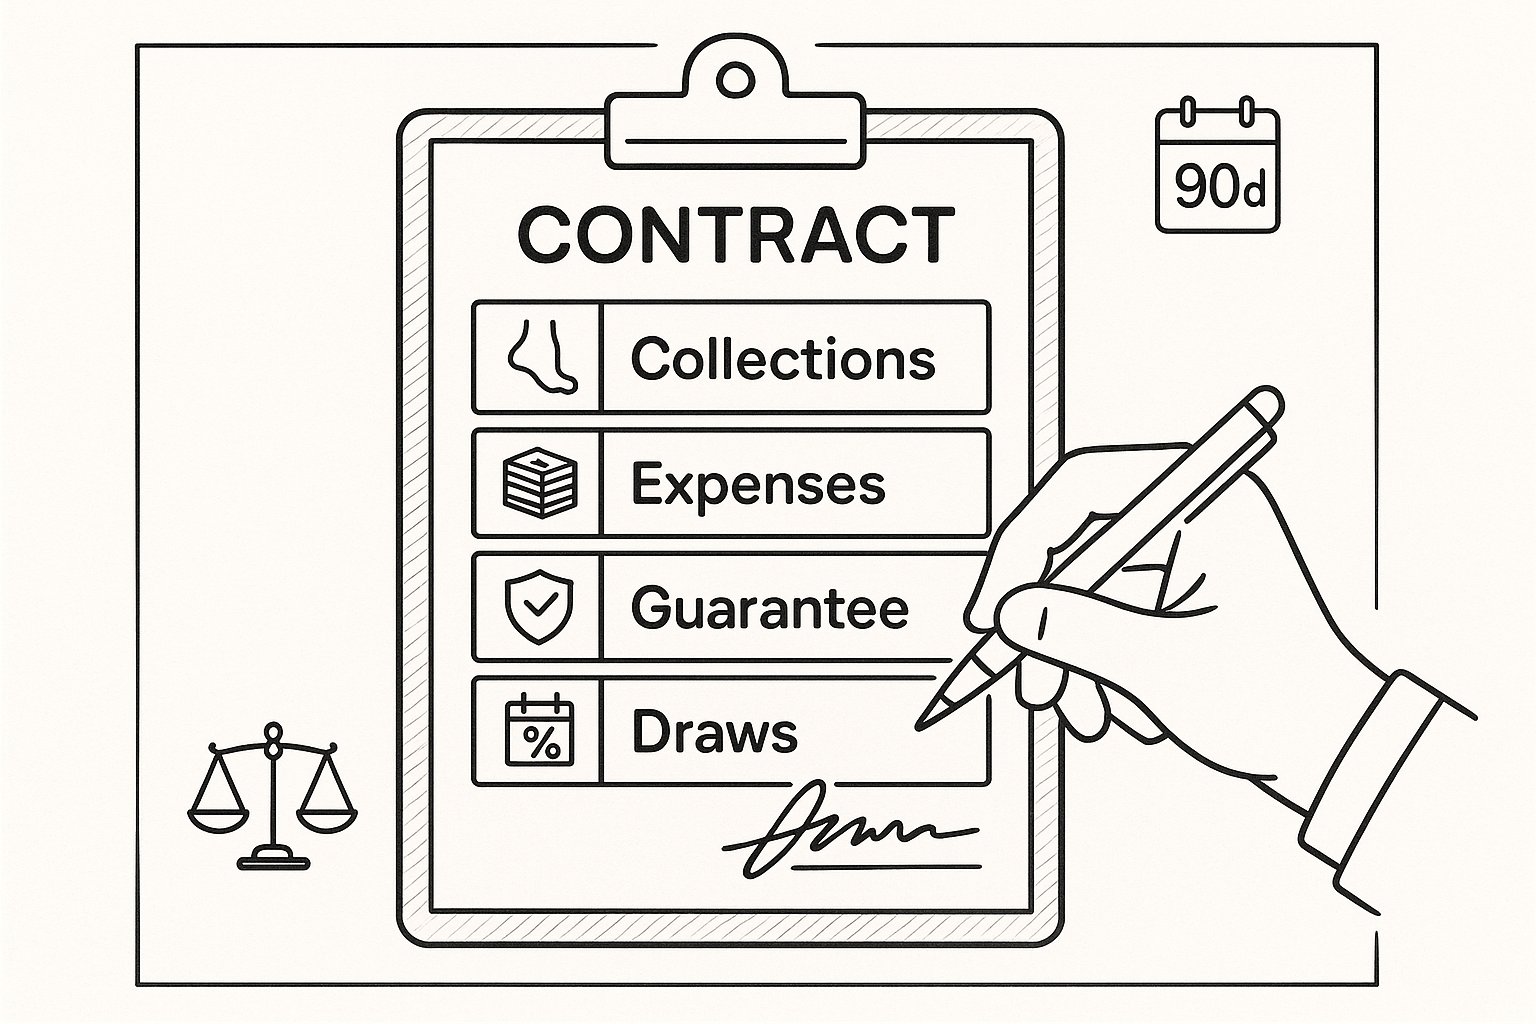
Compensation clauses are where many disputes originate. We focus on clarity: how you’re paid, how production is calculated, who deducts expenses, and what happens after termination.
Compensation structure basics: Common models include base salary (guarantee), production splits (percentage of collections or net revenue), percentage-of-collections after expenses, daily guarantees with periodic true-ups, and tiered bonuses tied to productivity thresholds. Each model shifts different risks to the associate or the employer. A flat salary transfers revenue risk to the employer: production-based compensation transfers more risk to you but can increase upside if well-structured.
Key protections to demand:
- Clear definition of “collections” vs “charges”: Is production measured by billed charges, allowed amounts, or actual cash collected? Ambiguity here costs providers significant sums.
- Timing and frequency of pay: Specify pay periods, how and when collections-based true-ups occur, and the accounting period for production calculations.
- Expense deductions: If the contract deducts expenses before calculating your percentage (e.g., payor write-offs, overhead allocation, credentialing fees), list each deductible item with caps or a firm percentage cap on administrative deductions.
- Collections credit: Define when a patient is credited to you (initial visit? ongoing care?) and who retains credit after termination.
- Advances/draws: If you receive a draw, define reconciliation terms, interest, repayment schedule, and permissible offsets (e.g., whether the employer can recoup draws from final paychecks).
Compensation fairness: We recommend setting minimum guarantees for the first 6–12 months with a clear conversion to production split thereafter. For podiatrists performing surgery, ensure the contract separately addresses facility fees, global surgery bundles, and call pay.
Regional tendencies: In higher cost-of-living areas or markets with hospital consolidation, base guarantees tend to be higher, and production splits are more employer-favorable. In competitive suburban markets, practices may offer more attractive splits or faster partnership tracks.
Practical clause examples (conceptual): A “collections” definition limited to cash collected by the practice within 90 days of billing, with employer bearing the cost of write-offs for uncollectible balances above a capped percentage: or a production split where the associate receives 35% of collections up to $X and 45% thereafter, with no deductions for administrative fees beyond a 10% fixed clinic fee.
Employment Vs Independent Contractor: Classification Risks And Consequences
Whether you’re classified as an employee (W-2) or an independent contractor (1099) affects tax withholding, benefits, malpractice coverage, and legal rights. Misclassification is an increasing enforcement priority for federal and state agencies.
Legal tests: States and federal agencies use varying factors to determine status, control over working hours and methods, who provides tools and office space, whether the provider is integrated into the employer’s business, and whether the arrangement is temporary. The IRS, state labor departments, and the Department of Labor all apply slightly different tests. California’s AB5-era residuals and Texas’s more employer-friendly tests are examples of how state law diverges.
Consequences of misclassification:
- Back taxes, penalties, and interest: If the state or IRS reclassifies you, the practice may be liable for unpaid payroll taxes; some states can also look to the provider for unpaid obligations in certain circumstances.
- Wage-and-hour claims: Misclassified providers may lose access to overtime or wage protections where applicable.
- Benefits and insurance gaps: Contractors usually must procure their own malpractice, health, and disability coverage. If misclassification is found, employers may be required to provide retroactive benefits or coverage.
- Regulatory compliance and licensing exposure: Some states restrict non-owners’ ability to bill under certain arrangements or impose fee-splitting prohibitions.
Best practices:
- If classified as a contractor, require the agreement to state that you control clinical methods, provide your own liability insurance, and retain the right to perform services for others, but ensure this matches actual practice. False appearances of control won’t protect against reclassification.
- Use incorporations properly: Professional corporations (PCs) or LLCs can provide a layer between you and the contracting entity, but they’re not a shield against misclassification scrutiny if the substance indicates employment.
Practical note for providers relocating: States vary in their enforcement of independent contractor status. For example, Massachusetts and California have stricter independent contractor rules in certain contexts, while some states defer more to contract language. Always consider local enforcement trends and consult counsel if the compensation differential between employee and contractor status is significant.
Noncompetes, Nonsolicits, And State-Specific Differences You Must Know
Restrictive covenants are among the most consequential provisions in provider agreements. Their enforceability varies widely by state and profession.
General trends: Several states have tightened restrictions on noncompetes (especially for lower-wage workers), some have enacted near-total bans, and courts continue to scrutinize breadth and duration. For licensed health professionals, many states treat noncompetes more strictly due to patient access concerns, but the outcome depends on each state’s public policy, statutory law, and case precedents.
State-by-state considerations (practical highlights):
- California: Noncompetes are largely unenforceable except in narrow sale-of-business scenarios. This gives providers greater mobility but requires careful attention to nonsolicit and trade-secret protections that practices may rely on in their place.
- Texas and Florida: More likely to enforce reasonable noncompetes if geographic scope and duration are narrow and the employer shows legitimate business interests.
- New York and Massachusetts: Courts enforce noncompetes when tailored to protect patient relationships and goodwill, but expect rigorous tailoring: overly broad covenants are struck down.
- Illinois and Washington: Recent legislative activity has limited noncompetes for low-wage workers and added notice requirements; healthcare professionals face mixed results across courts.
Podiatry-specific issues:
- Patient ownership: Some states consider patient choice paramount: covenants that effectively block a provider from treating former patients at a nearby location for an extended period are more likely to be scrutinized.
- Professional ownership and fee-splitting restrictions: States that prohibit non-physician ownership in medical practices sometimes impact how noncompetes are framed: employers may try to secure restrictive covenants as the primary protection for practice goodwill.
Nonsolicit vs. noncompete: Nonsolicit provisions that prohibit calling or directly soliciting patients are more likely to be enforceable if time-limited and narrowly drafted. Blanket prohibitions on treating former patients at new locations are riskier and may run afoul of public policy in some states.
Negotiation strategy:
- Narrow geographic scope and reasonable duration (commonly 6–24 months, depending on the state and specialty).
- Carve-outs for returning to work in a hospital, academic setting, or underserved area.
- Liquidated-damages clauses or garden-leave pay instead of injunctive relief, where enforceable.
- Mutual noncompetes are rare but can be requested to level the playing field.
Final point: Because state law differs dramatically, never accept a standard-form restrictive covenant without a jurisdiction-specific review. We evaluate both statutory law and recent appellate decisions when advising on enforceability and practical edits.
Malpractice Insurance, Tail Coverage, And Liability Allocation
Malpractice coverage terms can be confusing and have material financial consequences. We focus on understanding who provides what, and what you’ll owe if the relationship ends.
Types of coverage:
- Occurrence policies: Cover acts that occur during the policy period, even if claims are reported later. If the employer provides occurrence coverage, you generally aren’t required to purchase tail coverage upon separation.
- Claims-made policies: Cover claims made during the policy period. If a claims-made policy is used, tail or extended reporting coverage is often necessary to protect you for incidents that occurred while you practiced there but are claimed after termination.
Who pays for tail coverage? Practices sometimes require associates to obtain tail coverage at their own expense upon termination, especially if the associate was covered under an employer-provided claims-made policy. In some markets (particularly hospital employment), employers provide occurrence coverage or pay for tail if they terminate without cause. Negotiate who pays, and seek indemnity protection or a shared-cost formula if the employer declines to pay for tail.
Coverage for board complaints and administrative proceedings: Not all malpractice policies cover defense costs for licensing board investigations or administrative proceedings. Confirm whether the policy explicitly covers regulatory defense, including subpoenas, board hearings, and license reinstatement costs. If not included, negotiate separate coverage or a contractual employer obligation to defend and indemnify.
Vendor and group policies: Large groups and hospitals often have master policies; independent contractors usually must provide their own professional liability policies that meet minimum limits. Make sure limits meet state requirements and consider purchasing higher coverage if you perform surgery or hospital work that increases risk exposure.
Indemnity and risk allocation: Contracts may include broad indemnity language shifting liability to the associate for negligence or regulatory violations. Limit indemnity to willful misconduct or gross negligence and avoid clauses that require you to indemnify the employer for routine employer-level loss.
Practical examples: For podiatrists who do surgery, we recommend minimum limits that reflect risk (e.g., higher aggregate limits for operative practice), occurrence coverage if available, and employer-funded tail if the practice uses claims-made policies.
Termination, Repayment Obligations, Buyouts, And Patient Records/Continuity Of Care
Termination provisions determine what happens to your income, debts, and patients if the relationship ends. Focus on fairness and continuity of care.
Termination types and notice: Contracts commonly allow termination for cause (immediate) and without cause (with notice). Negotiate for at least 30–90 days’ notice for without-cause termination, and narrow the definition of cause. Define cure periods for alleged performance failures and require written notice with specifics.
Repayment obligations and clawbacks: Employers often seek to recoup signing bonuses, recruitment expenses, or training costs if you leave within a certain time. Limit repayment to a pro rata schedule, cap the amount that can be recouped, and exclude ordinary business costs. Ensure any repayment obligation is limited to reasonable, documented costs and that interest rates or withholding practices are specified.
Buyouts and partnership exit mechanics: Buy-in agreements should specify valuation methods (e.g., EBITDA, trailing revenue multiples), the treatment of goodwill, and the timing of buyouts. Avoid vague “fair market value” terms without an agreed valuation process. Include dispute resolution (independent appraiser) and protection against unilateral price manipulation.
Patient records and continuity of care: Clarify who retains patient records and the process for transferring care. Many states require providers to maintain access to patient records for a defined period and to notify patients about continuity-of-care options. Ensure the contract states that you may retain copies of your own medical records for continuity and regulatory compliance, and set a timeline and cost structure for record transfer or copying.
Post-termination collections: Specify how collections on your former patients will be allocated after termination and for how long you will receive credit. If the practice continues to bill for services you rendered, define the split and timeline. Also address responsibility for refunds, chargebacks, and payer audits post-termination.
Restrictions on future practice: If a noncompete applies, ensure there are carve-outs for hospital work, academic positions, or underserved areas. Where the employer seeks injunctive relief, negotiate a liquidated damages alternative or garden-leave pay to avoid career-stopping injunctions.
Practical scenario: If you leave because of a practice sale, confirm that patient records transfer with the practice sale and that any outstanding collections tied to your panel are either paid out or handled under a pre-agreed formula to avoid surprise clawbacks.
Negotiation Checklist: Red Flags, Practical Edits, And When To Consult An Attorney
This checklist focuses on practical edits that protect compensation, licensure, and the ability to keep practicing.
Red flags to watch for:
- Undefined “collections” or “net revenue” formulas.
- Unlimited recoupment rights for advances or bonuses.
- Mandatory independent contractor status that conflicts with actual control over your schedule or methods.
- Broad noncompetes with multi-state reach and long durations.
- Employer-provided claims-made malpractice with no tail coverage commitment.
- Indemnity language that shifts routine employer liability to you.
- No audit rights or opaque reporting timelines.
Practical edits we commonly negotiate:
- Define production: an enumerated list of revenue types that count, timing for collections accounting, and caps on administrative deductions.
- Limit recoupments: pro rata repayment schedule for signing bonuses and draws: prohibition on withholding final salary beyond state law limits.
- Modify classification language: where contractor status is required, include true control over hours, ability to treat outside patients, and clear tax indemnity language (but ensure facts align).
- Tail coverage clause: employer pays tail if terminated without cause, or provides occurrence coverage; otherwise, the employer pays a negotiated percentage of the tail cost if terminated for convenience.
- Narrow restrictive covenants: geographic and temporal limits, carve-outs for hospital employment, and demonstrable patient-based protection only.
- Audit and transparency: quarterly statements, a right to an independent CPA audit within a defined window, and dispute-resolution steps.
When to consult an attorney:
- If compensation formulas are ambiguous or have large deductions.
- If the contract includes a noncompete, nonsolicit, or customer-assignment clause with a broad scope.
- When malpractice coverage is claims-made, and the employer won’t cover tail.
- If the agreement requires a wide indemnity or hazardous recoupment terms.
- Any time you’re asked to sign a professional services agreement that redirects billing, records, or patient ownership to the employer.
We recommend a targeted attorney review focusing on: (1) compensation mechanics and audit rights, (2) restrictive covenants and post-termination practice rights, (3) malpractice and indemnity allocation, and (4) classification risk. Our practice aims to produce concise, state-specific edits that preserve relationships while protecting providers’ careers.
Conclusion
A contract shapes your professional life in measurable ways: pay, scope of practice, liability exposure, and even where you can see patients after you leave. Across states, the legal treatment of noncompetes, contractor classification, malpractice tail obligations, and patient-records rules varies, and those differences materially affect negotiation strategy. We recommend treating every agreement as negotiable, insisting on transparent compensation formulas, limiting clawbacks, securing malpractice protections, and narrowing restrictive covenants to what’s necessary and enforceable in your state. When key terms are ambiguous or carry outsized risk, consult an attorney who understands both the law and the operational realities of podiatry practice. We’ve reviewed thousands of contracts nationwide: when you need a focused, state-specific review, we’re ready to help.
Frequently Asked Questions about Podiatrist Contract Attorney Services
What types of agreements do podiatrists commonly sign, and how do they differ?
Podiatrists typically sign employment agreements (W-2), independent contractor agreements (1099), professional service contracts, affiliation/medical direction agreements, and buy-in or partnership agreements. Each defines compensation, liability, practice control, and post-termination obligations differently, impacting autonomy and legal responsibilities.
Why is it important for podiatrists to understand restrictive covenants in their contracts?
Restrictive covenants, such as noncompetes and nonsolicits, affect where and how podiatrists can practice after leaving a job. Their enforceability varies widely by state and specialty, influencing career mobility, patient relationships, and legal risks, making careful review and negotiation crucial.
When should a podiatrist consult a contract attorney?
Consult an attorney if the contract has ambiguous or unfavorable compensation formulas, broad noncompete or nonsolicit clauses, claims-made malpractice coverage without tail provisions, overly broad indemnity terms, or if billing, patient records, or practice control are unclear or shifted to the employer.


